
R
C
M
E
A
S
Y
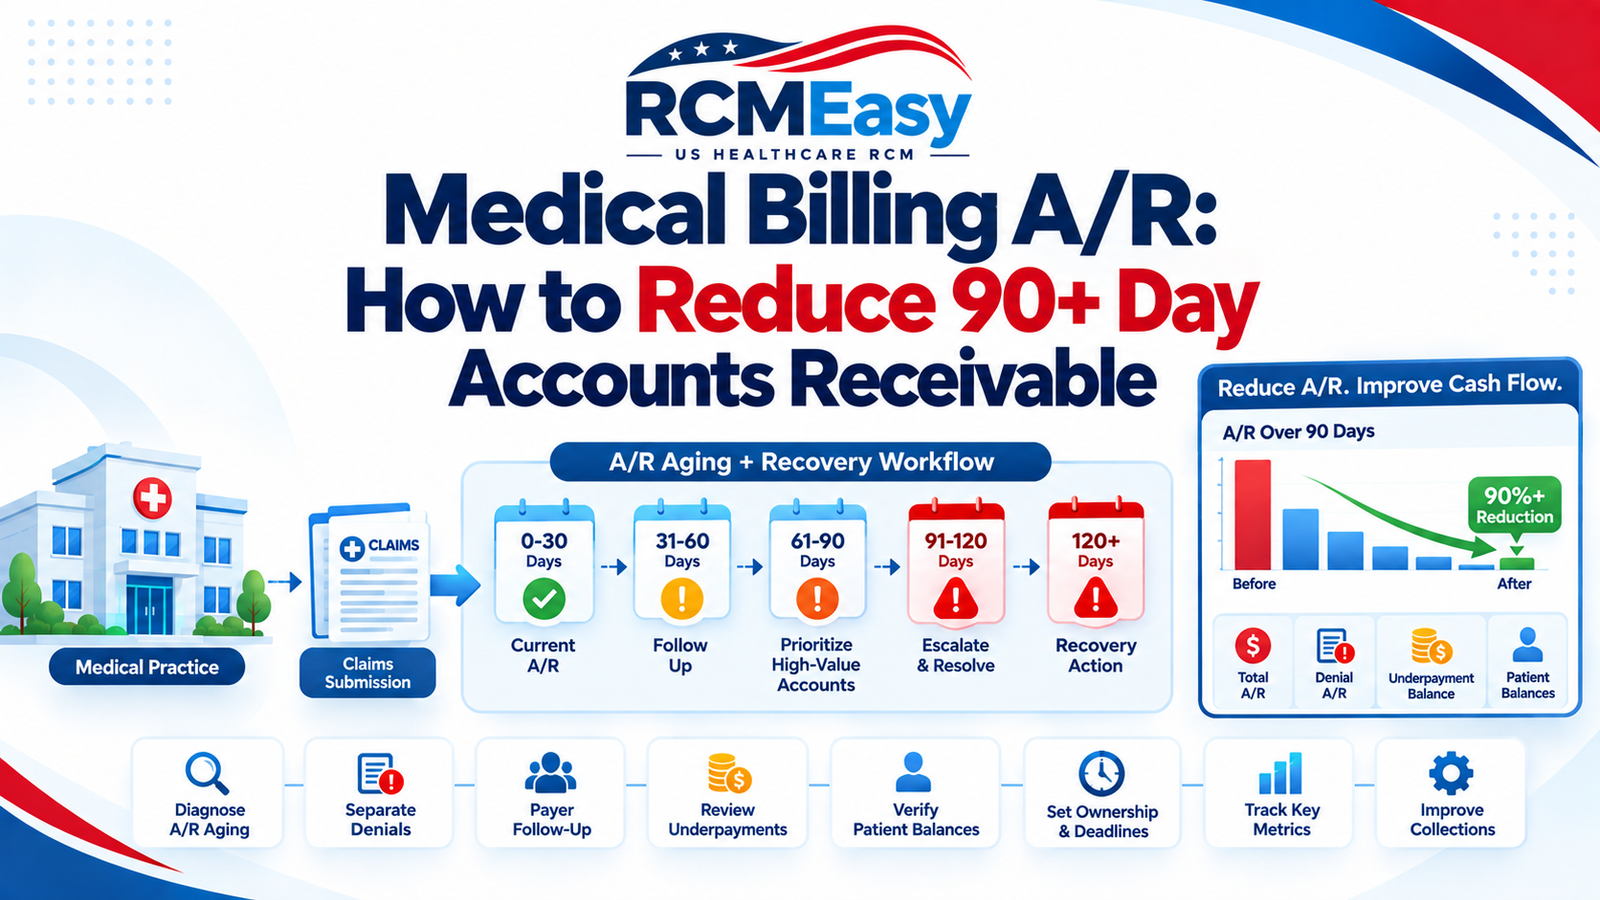
Medical Billing A/R: How to Reduce 90+ Day Accounts Receivable
Old A/R is a collection of unresolved problems. A 95-day balance may be waiting on a payer, stuck in an appeal, underpaid, denied or sitting with the patient.
Effective medical billing A/R management starts with segmentation, ownership and deadlines.
A/R Aging Framework
| Bucket | Primary action |
|---|---|
| 0-30 | Confirm submission and expected processing |
| 31-60 | Check status and missing information |
| 61-90 | Escalate unresolved claims |
| 91-120 | Prioritize value, deadline and recovery |
| 120+ | Intensive recovery or policy-based resolution |
Build a Clean A/R Inventory
For each open balance capture patient, payer, date of service, claim status, amount, expected reimbursement where available, last action, next action and deadline.
Prioritize More Than Age
Aging is useful but should not be the only rule. Prioritize high-value claims, approaching deadlines, systemic causes and balances with a realistic recovery path.
Insurance Follow-Up
Confirm receipt, adjudication status, pending information and next steps. Record payer reference numbers and avoid repeated calls that do not move the claim forward.
Denials
Separate denials from routine A/R. Use remittance information and payer context to choose correction, resubmission, appeal or another action. X12 maintains current CARC and RARC lists.
Underpayments
Compare actual payment with expected reimbursement when reliable contract information exists. Validate the contract before labeling a variance recoverable.
Patient Balances
Once insurance responsibility is resolved, use a consistent statement and follow-up policy. Patient balances need the same process discipline as payer A/R.
Escalation
Create rules for high-value claims, repeated payer delays, appeals approaching deadlines and accounts with multiple unsuccessful contacts.
Write-Off Review
Write-offs should follow documented policy. A claim should not become uncollectible simply because staff ran out of time.
Daily A/R Workflow
- Review new balances.
- Review high-value 90+ balances.
- Work payer status accounts.
- Process denials and appeals.
- Check underpayment exceptions.
- Update patient balances.
- Document next action and deadline.
Weekly Dashboard
| Metric | Purpose |
|---|---|
| Total A/R | Overall exposure |
| A/R over 90 | Aging risk |
| Denial A/R | Recoverable revenue |
| Underpayment balance | Contract variance |
| Unworked accounts | Capacity risk |
| Appeals pending | Recovery pipeline |
RCMEasy’s accounts receivable management covers insurance follow-up, old debt recovery, patient balances and A/R analytics.
Frequently Asked Questions
How do I reduce 90+ day A/R?
Build a clean inventory, prioritize high-value and deadline-sensitive accounts, separate denials, work payer follow-up and escalate unresolved balances.
Should every old claim be appealed?
No. Review the reason, deadline, evidence and recovery probability first.
Is there a universal healthy aging profile?
No. Compare your own trend and segment by payer, specialty and patient responsibility.
Need an A/R Cleanup Plan?
Contact RCMEasy for an A/R health check.
Sources
Last reviewed: September 3, 2026.
Related RCMEasy guide: Continue with this revenue cycle resource.
Segment A/R by Cause
An aging report tells you how old a balance is. It does not tell you why the balance is unpaid. Add categories such as pending payer claim, denial, underpayment, authorization issue, patient responsibility, missing information and other payer delay.
High-Value A/R Workflow
- Confirm claim receipt.
- Review adjudication status.
- Check denial or pend reason.
- Validate documentation and authorization.
- Calculate expected reimbursement when possible.
- Escalate if the payer is not responding.
- Document the next action and deadline.
Use Aging With Deadlines
A 45-day claim with an appeal deadline approaching may be more urgent than a 100-day balance with a clear recovery path. Combine age, value, deadline and status when prioritizing.
Patient A/R
Separate insurance and patient balances. Patient collections should follow the practice’s financial policy and applicable requirements. Clear statements and consistent communication reduce avoidable confusion.
Management Reporting
Report total A/R, A/R over 90 days, denial A/R, top payer balances, underpayment balances, unworked accounts and appeals pending. Add trends so leadership can see whether the problem is improving.
When to Escalate
- High-value balance near a deadline
- Repeated payer contacts without progress
- Potential underpayment
- Appeal awaiting response
- Systemic payer issue
For a broader view of leakage that often sits inside aging A/R, read the medical billing revenue leakage audit.
Related RCMEasy guide: Review the medical billing KPI guide and revenue leakage audit.
30-Day A/R Cleanup Sprint
- Extract every open balance.
- Separate payer, denial, underpayment and patient accounts.
- Prioritize 90+ day high-value balances.
- Assign a next action and deadline.
- Escalate unresolved payer issues.
- Review results weekly.
Prevent New Aging
A/R cleanup will not last if the front end remains weak. Pair recovery work with eligibility, authorization, charge capture, claim-edit and denial-prevention controls.

